
People with OCD experience the symptoms of "obsession", which are defined as recurrent persistent ideas, thoughts, images, or impulses. To reduce anxiety and find relief from these unrelenting obsessions, a person may develop "compulsions" or behaviours.
Obsessive compulsive symptoms are also found in people diagnosed with other psychiatric and neurological disorders, such as Tourette's syndrome, Autistic Spectrum Disorder, epilepsy, head trauma and front ear lobe lesions. These signs and symptoms are distressing, time consuming and significantly interfere with a person's normal routine, work, or social activities and relationships.
People with OCD may have comorbid depression where they worry incessantly, often overwhelmed by repetitive negative thoughts.
Additional Resources
NHG_Obsessive Compulsive Disorder.pdf
NHG_Obsessive_Compulsive_Disorder_Chi.pdf
NHG_Obsessive_Compulsive_Disorder_Mal.pdf
NHG_Obsessive_Compulsive_Disorder_Tam.pdf
Risk factors
Several factors can contribute to the risk of developing OCD:

Genetics:
There is evidence that OCD has a genetic component and it often runs in families.
Brain chemistry:
Serotonin is a chemical found in our brain cells that help to transmit information from one brain cell to another. Studies have shown that there is an imbalance of serotonin in the brains of people with OCD.
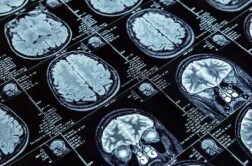
Brain circuitry:
Brain imaging studies in individuals with OCD have shown increased activity and blood flow in specific parts of the brain.

Stress/Life events:
Important life events such as bereavement or stress may trigger OCD symptoms in people who may be susceptible to develop the condition. Other triggers, including positive life events such as the birth of a child, are also, potential contributors to the eruption of the underlying condition.
Infection:
Some rare cases of OCD in children and young people have started after severe streptococcal or other infections. These infections may trigger OCD symptoms in children and young people who have a genetic predisposition to develop the condition.
Common obsessions include:

- Irrational fears of contamination from dirt or germs.
- Fear of hurting someone.
- Distressing sexual or religious thoughts.
- Desire to hoard or a need for symmetry and exactness.
Common compulsions include:

- Checking,
- Cleaning and washing,
- Counting,
- Hoarding,
- Mental ruminations.
A person with Hoarding Disorder:

- Has great difficulty discarding or parting with possessions, regardless of their actual value.
- Experiences distress when discarding the items due to the perceived need to save the items.
- Accumulates items until they congest and clutter living areas.
- Shows significant social and occupational impairment, a lack of self-care and increasingly unable to cope with daily living which inevitably affects self and others.
OCD can be successfully treated, and evidence shows that the sooner it is detected, the better the treatment outcomes are likely to be. A combination of medication and behavioural therapy has been found to be effective in significantly reducing the symptoms of OCD.
Medication:
Medication may be prescribed before or during behaviour therapy if there is indication of severe depression. Drug treatment after behaviour therapy may be prescribed if the therapy has been only moderately effective despite good cooperation. The use of antidepressants has proven to be effective in the treatment of OCD.
Cognitive Behavioural Therapy (CBT):
The mainstay of psychological treatment is CBT, where the individual is deliberately exposed to obsessional cues, and then prevented from engaging in the associated repetitive behaviour. With repeated and prolonged exposure to triggers, habituation eventually takes place. Exposure tasks are arranged hierarchically, with treatment commencing with the least anxiety-provoking situation and progressing rapidly through the hierarchy. Ruminations are more difficult to treat. Aversion conditioning such as thought stopping may be helpful. In addition, it is also useful to teach the individual ways of coping with anxiety, anger and stress. He will be encouraged to set other targets in life so as to develop a healthier lifestyle.
The combination of CBT and medication increases treatment efficacy. It is important to involve the family in the management of individuals with OCD. Family members are often ignorant about the disorder and may be drawn into the patient's rituals.

Obsessive-Compulsive Disorder (OCD) Service
IMH provides treatment and care for persons who have Obsessive-Compulsive Disorder (OCD).
For those with severe or treatment-resistant OCD who have not responded to adequate trials of both medication and Exposure and Response Prevention (ERP) therapy, IMH also offers a tertiary outpatient OCD Service under its Department of Mood and Anxiety. Our multidisciplinary team of psychiatrists, clinical psychologists, a family therapist, and a case manager provides intensive, specialised treatment for adults with severe, treatment-resistant OCD.
With comprehensive assessments and a range of treatment options tailored to each patient's needs – including pharmacological, psychological, occupational, and family therapies – our OCD Service multidisciplinary team supports patients in their recovery journey through close monitoring via a collaborative approach.
Referral Process:
- If you are a patient of IMH currently and are interested to be seen by our OCD Service team instead, please discuss with your IMH psychiatrist about your suitability.
- If you are not a patient of IMH currently, please ask your attending psychiatrist about your suitability for this service, and for a referral to IMH's OCD Service.
- If you are referred to the OCD Service, a case manager will contact you to conduct an initial triage assessment over the phone.
- Your case will be reviewed by our multidisciplinary team to determine suitability for the OCD Service.
- If suitable, you will be scheduled for a first visit appointment.
First Visit (120 minutes):
- You will meet our OCD Service multidisciplinary team, which comprises a psychiatrist, clinical psychologist, medical social worker and case manager. This allows us to better understand your needs as a team, while reducing the need for you to repeat difficult or upsetting experiences. This also helps us to develop the most appropriate treatment plan for you.
- A comprehensive assessment will be conducted by the psychiatrist and clinical psychologist. These in-depth assessments will take some time.
- For a more integrative consultation, you are encouraged to bring at least one next-of-kin who is familiar with your condition, and who will be supporting you in your recovery journey.
- Following the assessment, the team will work with you to determine the most appropriate course of treatment.

